

Quick answer:
A therapy practice is usually worth a multiple of its normalized earnings, adjusted for how reliably those earnings can continue after the owner leaves. Small, owner-operated practices are often valued using seller’s discretionary earnings (SDE). Larger group practices are more often valued using adjusted EBITDA. Revenue can provide a rough check, but revenue alone does not show staffing cost, owner dependence, payer risk, or profit.
If you are asking, “How much is my therapy practice worth?” the honest answer is a range, not a single number. The multiple matters, but the earnings base matters just as much. A buyer will also test whether clinicians, referrals, payer contracts, leadership, and operating systems will transfer.
How much is my therapy practice worth? Start with normalized earnings
The simplest version of the calculation is:
Normalized earnings × an appropriate market multiple = enterprise value
Enterprise value is the value of the operating business before adjusting for debt, excess cash, working-capital differences, and certain transaction expenses. The amount an owner ultimately receives can be lower or higher than enterprise value depending on those adjustments and the structure of the deal.
A credible valuation does not begin by choosing the highest multiple found online. It begins by defining what is being valued, the valuation date, the purpose, the standard of value, and the financial benefit stream being multiplied. The IRS describes the asset, market, and income approaches as the three generally accepted approaches to business valuation and calls for historical financials to be adjusted when needed so that the selected earnings or cash-flow measure matches the valuation method.
Should you use SDE or EBITDA?
Use SDE for a smaller, owner-operated practice
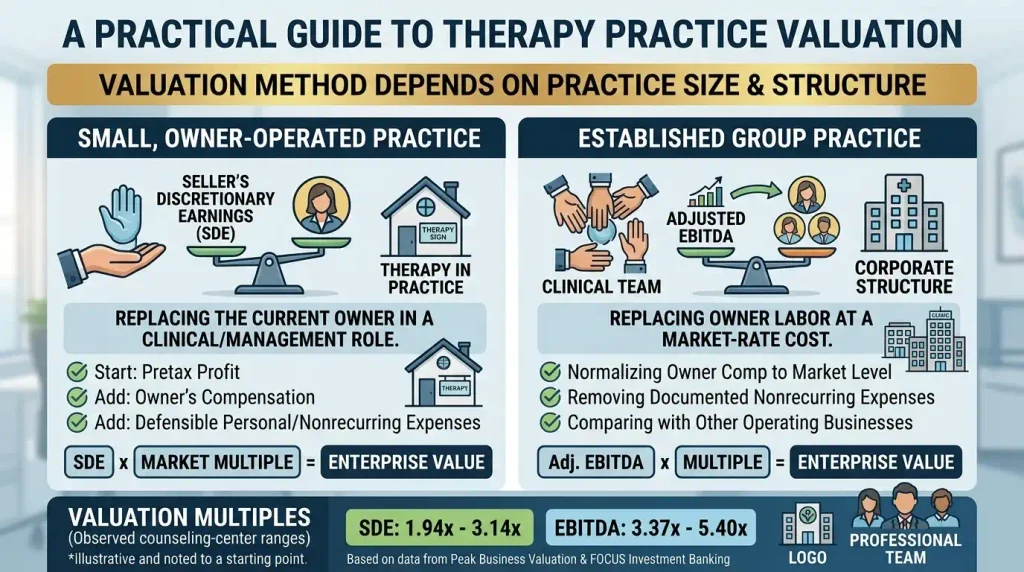
Seller’s discretionary earnings estimates the total financial benefit available to one working owner. It generally starts with pretax profit, then adds the owner’s compensation and defensible personal or nonrecurring expenses. SDE is useful when the likely buyer expects to replace the current owner in a clinical or management role.
An owner who carries a full caseload, handles supervision, manages hiring, and approves every financial decision has created a real business. The buyer, however, may also be buying a demanding job. SDE helps measure the economics of that owner-operator model.
Use adjusted EBITDA for a group practice with transferable management
EBITDA means earnings before interest, taxes, depreciation, and amortization. Adjusted EBITDA goes further by removing documented, nonrecurring expenses and normalizing owner compensation or related-party expenses to market levels.
EBITDA is more useful when a practice has several clinicians, reliable administrative systems, and enough management depth to operate without the founder doing all the work. It lets a financial or strategic buyer compare the practice with other operating businesses.
Do not switch between SDE and EBITDA multiples
An SDE multiple cannot be applied to EBITDA, or vice versa, without changing the result. The IBBA Market Pulse report reflects this market convention: transactions below $2 million in business value are reported as SDE multiples, while transactions from $2 million to $50 million are reported as EBITDA multiples. That is a broad private-company benchmark, not a therapy-specific rule, but it shows why the benefit stream must match the multiple.
| Practice profile | Common earnings measure | What the measure assumes |
| Solo or small owner-operated practice | SDE | A buyer may perform the owner’s clinical or management work |
| Established group practice | Adjusted EBITDA | Owner labor is replaced at a market-rate cost |
| Scaled, multi-site platform | Adjusted EBITDA | A management team and operating infrastructure remain after closing |
| Low-profit or asset-heavy practice | Asset or income analysis | A simple earnings multiple may not capture the relevant value |
The three valuation approaches
1. Market approach
The market approach compares the practice with similar businesses that have sold. A valuation professional may analyze private transaction databases and then adjust for size, margins, geography, payer mix, clinician model, growth, and owner dependence.
The strength of this method depends on the quality of the comparable transactions. A 30-clinician, management-led outpatient group is not comparable to a solo practice simply because both provide therapy.
2. Income approach
The income approach estimates the present value of expected future cash flow. It can be useful when historical results do not fully represent the future, but forecasts need careful testing. Small changes in growth, margins, risk, or the terminal value can move the answer materially.
The IRS cautions that an income approach relies on assumptions about future events and recommends confirming it, where possible, with market and cost evidence.
3. Asset approach
The asset approach considers the fair market value of assets minus liabilities. For many therapy practices, desks, laptops, and office furniture are not the main source of value. The more meaningful assets are often intangible: an assembled clinical team, operating systems, brand reputation, referral relationships, payer access, and goodwill.
Those assets deserve careful treatment. Client records are governed by privacy, consent, professional, and state-law requirements. Referral value also cannot be treated as a simple commodity. Legal counsel should review what can transfer and how.
What valuation multiples apply to a therapy practice?
Published benchmarks are useful for orientation, not as an offer. Peak Business Valuation reports the following observed counseling-center ranges from its private transaction data: 1.94× to 3.14× SDE, 3.37× to 5.40× EBITDA, and 0.40× to 0.69× revenue.
| Metric | Published counseling-center range | Best use | Main limitation |
| SDE | 1.94×–3.14× | Smaller owner-operated practices | Depends heavily on accurate add-backs and the owner’s role |
| EBITDA | 3.37×–5.40× | Established group practices | May not represent larger institutional transactions |
| Revenue | 0.40×–0.69× | High-level reasonableness check | Does not account for profit or staffing cost |
Institutional behavioral-health deals can trade at higher multiples, but they are a different market. FOCUS Investment Banking’s 2025 report places mental health and outpatient psychiatry add-ons at 4× to 8× EBITDA and scaled platforms at 10× to 14× EBITDA. Those ranges generally describe businesses with more scale, infrastructure, and buyer competition than a typical local group practice. Applying a platform multiple to a founder-dependent practice would overstate value.
For a fuller explanation of the ranges and their limits, read What Multiple Do Therapy Practices Sell For?
What raises or lowers a therapy practice’s value?
Founder dependence
Buyers ask what changes when the founder steps away. A practice tends to be more transferable when the founder has reduced their personal caseload, delegated supervision and operations, documented decisions, and built referral channels around the organization rather than one person.
If the founder is the main clinician, rainmaker, supervisor, recruiter, and culture carrier, the buyer may discount earnings or require a longer transition.
Clinician retention and recruiting
A full schedule is not durable if the clinicians producing the revenue plan to leave. Buyers will examine turnover, tenure, compensation, benefits, supervision, caseloads, employment agreements, contractor classification, recruiting time, and open positions.
Workforce risk is not theoretical. HRSA’s 2025 workforce report projects substantial shortages across multiple behavioral-health occupations and identifies burnout, reimbursement challenges, and scope-of-practice constraints as retention pressures. A practice that recruits well and retains clinicians without relying on the founder can reduce a buyer’s operating risk.
Payer mix and revenue quality
Paying source matters because two practices with the same revenue may have different reimbursement risk, collection timing, denial rates, and margins. Buyers often review:
· commercial insurance, Medicaid, Medicare, employee assistance, and private-pay mix;
· revenue concentration by payer;
· credentialing status and transfer requirements;
· contract rates and renewal history;
· days in accounts receivable, denials, refunds, and write-offs;
· documentation and billing compliance.
A diversified payer base is not automatically superior. A private-pay practice with strong demand and low acquisition cost may be attractive. A well-run in-network practice may have more predictable volume. The question is whether the economics are documented and likely to continue.
Referral concentration
A buyer will want to know where new clients come from and whether those sources will remain after a sale. Referral data should separate the founder’s personal relationships from channels owned by the practice, such as a recognized brand, search visibility, physician relationships, school partnerships, payer directories, or institutional contracts.
Do not identify clients or disclose protected health information in a marketing package. Aggregate operational data is usually enough for early analysis; counsel and compliance advisors should control later disclosures.
Financial quality
Clean financial statements make earnings easier to trust. Buyers will compare profit-and-loss statements with tax returns, payroll, bank records, billing data, and clinician-level production. Unsupported add-backs, mixed personal expenses, inconsistent accounting, or unexplained swings make the valuation harder to defend.
Management and operating systems
Documented intake, scheduling, credentialing, billing, quality, hiring, supervision, privacy, and compliance processes reduce reliance on informal knowledge. A capable clinical director or operations lead can be more valuable than a binder of policies nobody follows.
Growth quality
Buyers pay for earnings they believe they can keep, not for a forecast alone. Growth carries more weight when it is visible in completed hiring, demand by service line, capacity, signed leases, payer access, referral conversion, and repeatable marketing economics. A waitlist is only valuable if the practice can recruit clinicians and convert that demand into collected revenue.
Worked example: estimating enterprise and equity value
The following example is illustrative. It is not a valuation opinion or a promise of market value.
| Normalization item | Amount |
| Reported operating profit | $260,000 |
| Add: interest | $20,000 |
| Add: depreciation and amortization | $15,000 |
| Add: one-time office move | $25,000 |
| Add: documented personal expense | $10,000 |
| Subtract: market-rate replacement manager | ($80,000) |
| Illustrative adjusted EBITDA | $250,000 |
At an illustrative 4.5× multiple, the estimated enterprise value would be $1,125,000.
If the practice had $150,000 of debt to be repaid at closing and $50,000 of excess cash retained in the transaction, the simplified equity-value bridge would be:
$1,125,000 enterprise value − $150,000 debt + $50,000 excess cash = $1,025,000 estimated equity value.
That still is not the owner’s net proceeds. Taxes, transaction fees, working-capital adjustments, escrow, earnouts, rollover equity, and other negotiated terms can change the amount and timing of payment.
Why the highest headline offer may not be the best offer
A buyer can reach the same stated price with very different terms. Compare:
· cash paid at closing;
· seller financing;
· earnout conditions;
· rollover equity and its future liquidity;
· working-capital requirements;
· indemnity, escrow, and holdback provisions;
· the owner’s employment, compensation, and transition period;
· treatment of debt, cash, and transaction expenses.
IBBA’s Q3 2025 data show that deal structure changes with transaction size and that not every dollar of stated consideration is necessarily paid in cash at closing. Owners should compare expected, risk-adjusted proceeds rather than headline price alone.
How to prepare for a credible therapy practice valuation
1. Reconcile three years of financials. Align tax returns, profit-and-loss statements, balance sheets, payroll, and billing reports.
2. Prepare a trailing-12-month view. Buyers need current performance, not only the last completed tax year.
3. Build an add-back schedule. Attach an invoice, ledger entry, contract, or other support to every adjustment.
4. Map owner responsibilities. Estimate the market cost and time required to replace each clinical, supervisory, referral, and operating duty.
5. Measure clinician stability. Track headcount, tenure, turnover, open roles, compensation, caseload, and productivity without exposing client identities.
6. Analyze payer and referral concentration. Show revenue, collections, denials, and new-client sources by category.
7. Document the operating model. Include intake, scheduling, billing, credentialing, compliance, supervision, and management responsibilities.
8. Separate value from price and proceeds. Model enterprise value, equity value, deal structure, fees, and taxes as different figures.
Online calculators can help with early planning. A formal appraisal or advisor-led valuation becomes more important when a real buyer appears, partners hold different interests, financing is involved, or the practice has complex payer, staffing, or ownership arrangements. Therapy-specific guidance also recommends professional review as a transaction becomes real or more complex.
Frequently asked questions
What is the average value of a therapy practice?
There is no reliable average dollar value because practice size, earnings, owner involvement, clinician stability, payer mix, and buyer type vary widely. A more useful estimate starts with normalized SDE or EBITDA and applies a multiple supported by comparable transactions.
Can I value my therapy practice based on revenue?
Revenue can provide a rough reasonableness check, but it should not be the only method. Two practices with the same revenue can have very different clinician costs, overhead, denial rates, owner dependence, and profit.
Is a solo therapy practice sellable?
It can be, but the transferable value may be limited when revenue depends on the owner’s personal clinical work and relationships. Systems, brand reputation, referral channels, a careful transition, and any transferable staff or contracts may still create value.
What is the difference between practice value and sale proceeds?
Practice or enterprise value measures the operating business. Equity value adjusts for debt, cash, and agreed working capital. Net proceeds then account for taxes, fees, escrows, earnouts, and other deal terms.
How far in advance should I prepare for a valuation?
Start before you need to sell. A longer runway gives you time to clean financials, reduce founder dependence, improve retention, document referral channels, and show that changes are durable rather than last-minute.
Know the range before you negotiate
A valuation should explain the range, the assumptions behind it, and the risks a buyer will test. Therapy Practice Exit Report helps owners understand those questions before a transaction. If you are considering a sale or responding to an unsolicited approach, Olympic M&A advises healthcare and founder-led business owners on preparation, positioning, and transaction execution.



